

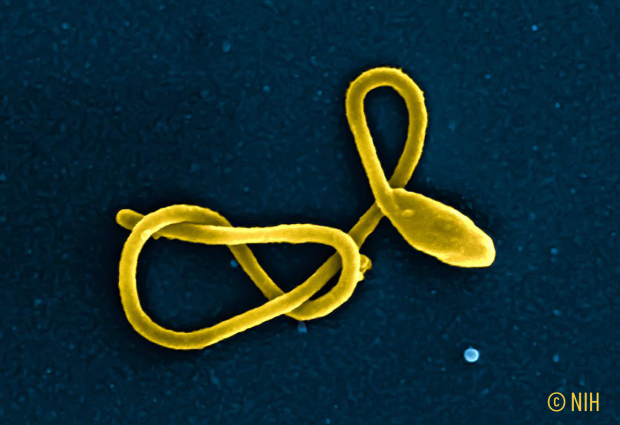
Severe viral haemorrhagic fever caused by viruses of the genus Orthoebolavirus.
Last updated on 30 September 2026
A severe viral haemorrhagic fever with a case fatality rate ranging from 25 to 90% (average case fatality rate of 50%) depending on the outbreak,¹˒² Ebola virus disease is caused by viruses of the genus Orthoebolavirus, of which only four (Bundibugyo, Sudan, Taï Forest and Zaire) have been associated with Ebola virus disease.³
Ebola first emerged in 1976 in outbreaks in South Sudan and the Democratic Republic of the Congo. Since then, 42 outbreaks have been reported in Africa, of which 31 were caused by Ebola virus (EBOV), also known as Ebola Zaire, and eight by Sudan virus (SUDV), resulting in 23,045 cases, including 14,885 deaths, and 956 cases, including 503 deaths, respectively.⁴
The sporadic nature of outbreaks suggests a probable zoonotic origin, although human-to-human transmission is possible.⁴
This is a zoonotic disease, with fruit bats of the family Pteropodidae serving as the natural hosts of the virus. Bats transmit the virus to mammals, particularly non-human primates, through contaminated fruit and their faeces. Animal-to-human transmission occurs through contact with infected animals, whether alive or dead.
Human-to-human transmission occurs through direct contact with the bodily fluids of an infected person, or indirectly through contaminated bedding, clothing or syringes.²˒⁵˒⁶ Sexual transmission has been observed but is extremely rare.³
Several rapid diagnostic tests are available, but none can distinguish SUDV from EBOV.⁷ The disease is generally diagnosed using RT-PCR or serology (ELISA testing). These tests should be performed on blood samples, or oral fluid samples when blood collection is not possible.³
The incubation period ranges from 2 to 21 days, and the virus cannot be transmitted before symptoms appear.
Symptoms develop suddenly in two phases: the dry phase and the wet phase. The dry phase includes symptoms such as fever, fatigue, muscle pain, headaches and a sore throat. The wet phase, which is the most contagious, is characterised by vomiting, diarrhoea, skin rashes, multiple organ failure, particularly kidney failure, and sometimes internal and external bleeding.⁵
The management of SUDV infections relies on supportive care, including oral or intravenous rehydration and symptomatic treatments.⁸
There are currently no approved treatments or vaccines for prevention, nor any specific treatment for Ebola disease caused by SUDV.⁸
Two multivalent vaccines, Ervebo® and Zabdeno®/Mvabea®, have been approved against Ebola virus disease caused by the Ebola Zaire strain (ZEBOV). In a phase III clinical study, the rVSV-ZEBOV vaccine candidate (Ervebo®) demonstrated good tolerability and efficacy, as well as high persistence of ZEBOV-specific antibodies beyond two years.⁹
However, these vaccines do not appear to provide cross-protection against SUDV,¹⁰ although a preclinical study demonstrated a protective immune response against SUDV induced by the multivalent vaccine Ad26.ZEBOV/MVA-BN-Filo (Zabdeno®/Mvabea®) in non-human primates.¹¹
Other multivalent vaccines targeting other filoviruses have been evaluated in early clinical trials. Among these, the cAd3-EBO vaccine exhibited reactogenicity and a dose-dependent immune response in a phase I clinical trial involving 20 participants.¹² In another phase I clinical trial, the ChAdOx1 biEBOV vaccine, administered intramuscularly to participants aged 18 to 55 years, demonstrated good tolerability.⁸
Monovalent vaccines against SUDV are currently under development. The rVSV-SUDV vaccine demonstrated efficacy in preclinical studies in non-human primates.¹³ Its tolerability and a rapid immune response, with antibodies persisting one year after injection, were demonstrated in healthy volunteers in a phase I randomised vaccine trial.¹⁴ A phase II trial conducted in Africa and the United States is currently recruiting participants.¹⁵ Its clinical efficacy and immunogenicity will be evaluated during an outbreak in the WHO-supported “TOKOMEZA SVD” vaccine trial in Uganda.¹⁶
Another monovalent vaccine, ChAd3-SUDV, showed sustained protection after macaques were infected with a lethal dose of Sudan virus.¹⁷ A phase I clinical trial was initiated, followed in 2024 by a phase II trial in Uganda, Kenya and the United States.¹⁸
In 2023, a phase I/II vaccine trial (Solidarity/Tokomeza Ebola Trial) was also launched in Uganda during a period between Ebola outbreaks to evaluate the tolerability and immunogenicity of the ChAd3-SUDV, ChAdOx1 biEBOV and rVSV-SUDV vaccine candidates against Sudan virus. Recruitment is currently ongoing, with the aim of enrolling 250 healthy volunteers in phase I and more than 2,000 in phase II.¹⁹
The US Food Drug and Administration (FDA) has approved two treatments against ZEBOV: Inmazeb®, a combination of three antibodies (atoltivimab/maftivimab, odesivimab), and Ebanga® (ansuvimab).²⁰ The efficacy of these products was demonstrated in a clinical trial involving nearly 700 participants, which showed a significant reduction in mortality compared with remdesivir.²¹ Other clinical trials are ongoing to evaluate Ebanga® and Inmazeb® in patients infected with ZEBOV.²²˒²³
Antivirals are also being investigated for the treatment of Ebola virus disease. Galidesivir, a broad-spectrum antiviral, showed antiviral activity against EBOV in preclinical studies and good tolerability in a phase I study in healthy volunteers.²⁴˒²⁵ Obeldesivir, administered 24 hours after infection, provided complete protection for 10 days in cynomolgus macaques that had received a lethal dose of SUDV.²⁶
Antivirals and monoclonal antibodies are currently being investigated for their activity against SUDV.

In early 2025, ANRS MIE was appointed to lead the CORC (Collaborative Open Research Consortium) on filoviruses and is set to become a WHO Collaborating Centre.
CORCs are international networks of research institutions whose mission is to strengthen global pandemic preparedness through collaborative research, knowledge sharing and the rapid development of countermeasures. An initial meeting, held on 13 February 2025, focused on therapeutic trials and priority research on medical countermeasures. Within the CORC, research priorities have been defined by ANRS MIE and WHO, and work is under way with all experts from the “CORC on filoviruses” to update the research priorities and gaps identified in the MARVAC consortium roadmap.
In March 2025, the ANRS MIE “Epidemic Monitoring and Response” division activated a level 1 Outbreak Response unit on filoviruses. This permanent unit includes scientific monitoring, the first editions of which will focus on Marburg virus currently circulating in Tanzania and Sudan Ebola virus, which is responsible for an ongoing outbreak in Uganda.
In 2024, ANRS MIE established a coordinated action on viral haemorrhagic fevers chaired by Sylvain Baize, Marie Jaspard and Abdoulaye Touré. This group for discussion and strategic reflection focuses particularly on scientific research on filoviruses and aims, through its working groups (therapeutics, wildlife, vaccines), to generate research projects through international collaborations, primarily with our partners in Africa.